Organismal Biology · Unit 3: Supply and exchange
Carrying Oxygen and Carbon Dioxide
Plasma dissolves very little oxygen, so how does blood carry enough of it, and how does it get carbon dioxide back to the lungs? This lesson reads the oxygen dissociation curve, follows what shifts it, from Bohr's 1904 dog-blood paper to fetal hemoglobin's weaker response to BPG, and compares carriers across animals, from horse myoglobin to icefish with no hemoglobin at all. Afterwards you can read saturation and P50 off a curve, predict a shift, calculate oxygen content and oxygen use, and describe the three ways carbon dioxide travels.
Watch first Hemoglobin Loads Flat, Unloads Steep · 2:50
A litre of your arterial blood carries about 200 mL of oxygen. If that blood were plasma alone, it would carry about 3 mL.
Oxygen dissolves poorly in water, and plasma is mostly water. This lesson is about how blood makes up the difference: how a carrier picks up oxygen in the lungs and releases it in tissues, what makes it release more, how different animals solve the same problem, and how carbon dioxide gets back the other way. It builds on gas exchange, where oxygen crosses into the blood, and on blood and vessels and the heart, which move it.
The idea: a carrier with an S-shaped curve
Gases move by diffusion from where their partial pressure is high to where it is low. Partial pressure is the share of a gas mixture’s pressure due to one gas, written PO2 for oxygen and measured here in mmHg (1 Torr is essentially the same unit). In an adult human at rest, arterial PO2 is about 100 mmHg and the PO2 of blood returning from the body is about 40 mmHg.
The amount of oxygen that dissolves is proportional to PO2: about 0.003 mL per dL of blood for each mmHg. At 100 mmHg that is 0.3 mL per dL, far too little. In mammals, almost all the oxygen rides on hemoglobin, an iron-containing protein packed inside red blood cells. Each human hemoglobin molecule has four chains, two alpha and two beta in the adult form, and four oxygen-binding sites.
The saturation of hemoglobin is the fraction of its binding sites that hold oxygen. Plot saturation against PO2 and you get the oxygen dissociation curve. For adult human blood it is S-shaped, or sigmoid. Above about 60 mmHg it is nearly flat: blood in the lungs loads almost fully, and a modest fall in lung PO2 costs little. Between about 10 and 40 mmHg it is steep: a small fall in tissue PO2 releases a large amount of oxygen.
The P50 is the PO2 at which hemoglobin is half saturated. It measures affinity, how tightly the carrier holds oxygen, in reverse: a higher P50 means lower affinity. In a standard model of human blood at 37 degrees C, pH 7.4 and a carbon dioxide pressure of 40 mmHg, P50 is 26.8 mmHg.
The S shape comes from cooperative binding: oxygen binding at one site makes the remaining sites of the same molecule bind more readily. How the four chains pass that change between them is told in protein binding and allostery. Think of a bus that fills slowly while it is empty and quickly once a few passengers are on, and empties the same way.
Worked problem: how much oxygen does the body use? Take an illustrative adult human at rest. Assume hemoglobin 15 g per dL, 1.34 mL of oxygen per g of fully saturated hemoglobin (a common working value; the theoretical figure is near 1.39), dissolved oxygen 0.003 mL per dL per mmHg, a steady state and a cardiac output of 5.0 L per min.
oxygen content = (1.34 x hemoglobin x saturation) + (0.003 x PO2) oxygen use = cardiac output x (arterial content - venous content)
- Arterial blood (saturation 98%, PO2 100 mmHg): bound = 1.34 x 15 x 0.98 = 19.70 mL per dL; dissolved = 0.003 x 100 = 0.30 mL per dL; total 20.00 mL per dL.
- Mixed venous blood (saturation 75%, PO2 40 mmHg): bound = 1.34 x 15 x 0.75 = 15.08 mL per dL; dissolved = 0.12 mL per dL; total 15.20 mL per dL.
- Difference: 20.00 - 15.20 = 4.80 mL per dL. The tissues took 4.80 / 20.00 = 24% of the oxygen offered.
- Fick principle: 5.0 L per min is 50 dL per min. Delivery is 50 x 20.00 = 1,000 mL per min; use is 50 x 4.80 = 240 mL per min.
Only 0.30 of 20.00 mL per dL, 1.5%, is dissolved. Notice too that three-quarters of the oxygen comes back unused. That venous reserve sits on the steep part of the curve, so tissues can draw on it in exercise, a point taken up in muscle and movement.
- Arterial (saturation 98%, PO2 100 mmHg)
- Mixed venous (PO2 40 mmHg)
- Difference, and share used
- Delivery (cardiac output x arterial content)
- Oxygen use (Fick principle)
- Dissolved share of arterial content
In this sketch: an illustrative adult human at rest, steady state, 1.34 mL O2 per g of fully saturated hemoglobin (a common working value; the theoretical figure is near 1.39), 0.003 mL per dL per mmHg dissolved, arterial saturation 98% and PO2 100 mmHg, and venous PO2 held at 40 mmHg whatever the venous saturation. Slider settings other than the worked values are not claims about any person.
Oxygen content is bound plus dissolved, and oxygen use is cardiac output times the arterial-venous difference. Lower pH or more carbon dioxide (the Bohr effect) shifts the curve right, and higher temperature and more BPG are separate effects that also raise P50; at the same PO2 the blood then holds less oxygen. No curve is drawn because the lesson gives no equation for it.
Shifting the curve: Bohr’s dog blood, temperature and BPG
In Copenhagen in 1903, Christian Bohr, working with Karl Hasselbalch and August Krogh, took fresh dog blood and exposed samples to gas at set oxygen pressures, measuring how much oxygen the blood bound. Then they raised the carbon dioxide in the gas and measured again at the same oxygen pressure. If carbon dioxide simply travelled alongside oxygen, the bound oxygen should not have changed. Instead, more carbon dioxide lowered oxygen binding, and the effect was largest at low oxygen pressures and small near full saturation.
That result showed a large effect of carbon dioxide on oxygen binding in dog blood, and it acts where it matters: in respiring tissue, carbon dioxide is high and PO2 is low. It did not say how carbon dioxide acts, since carbon dioxide also makes blood more acidic.
Today the Bohr effect names the fall in hemoglobin’s oxygen affinity when pH falls or carbon dioxide rises. Both shift the curve to the right, raising P50, so at the same PO2 the blood holds less oxygen and has released more. Two other changes also shift the curve right, and they are separate effects, not the Bohr effect:
- Higher temperature lowers affinity. Working muscle is warmer than resting muscle.
- More 2,3-bisphosphoglycerate (BPG), a small molecule made in red cells from a side branch of glycolysis, lowers affinity. Ruth and Reinhold Benesch reported this in 1967, as did Alfred Chanutin and Richard Curnish the same year. BPG binds preferentially to the deoxygenated form of hemoglobin.
Reverse any of these, with higher pH, less carbon dioxide, lower temperature or less BPG, and the curve shifts left, toward higher affinity.
Fetus, muscle, body size and icefish
The same problem of loading and unloading oxygen is solved differently in different places and animals.
The human fetus. Fetal blood picks up oxygen from the mother’s blood in the placenta (see animal reproduction), and it has higher affinity than adult blood: its curve sits to the left. Fetal hemoglobin has gamma chains in place of the adult beta chains. In 1970 H. Franklin Bunn and Robin Briehl showed that, with BPG removed and then added back at the same concentration, adult hemoglobin’s P50 rose about twofold while fetal hemoglobin’s rose less. Fetal hemoglobin still binds BPG; it responds less to it. Whole cord blood also had higher affinity than adult blood in a 1972 comparison by Enoki and colleagues.
Myoglobin. Myoglobin is a single-chain oxygen-binding protein in muscle. With one site there is no cooperation, and its curve is hyperbolic, rising steeply from zero and flattening early. Horse myoglobin in solution at 37 degrees C and pH 7.0 has a P50 of 2.39 Torr, roughly a tenth of the 26.8 mmHg modelled for human blood. Because myoglobin has such a low P50, it stays largely loaded until the PO2 inside muscle fibres is very low, so it can take up oxygen from blood and give it up when the PO2 falls, as in hard work. Keep in mind that one number comes from purified horse protein and the other from a model of human blood.
Body size. Among mammals, small species tend to have higher P50 values than large ones, a pattern described by Knut Schmidt-Nielsen and J. L. Larimer in 1958, though the trend is loose and differs among lineages. A mouse uses more oxygen per gram of tissue than an elephant (see size and scaling), and lower affinity favours unloading. Other animals have shifts linked to altitude, such as the bar-headed goose and the llama, whose hemoglobins are described in protein binding and allostery.
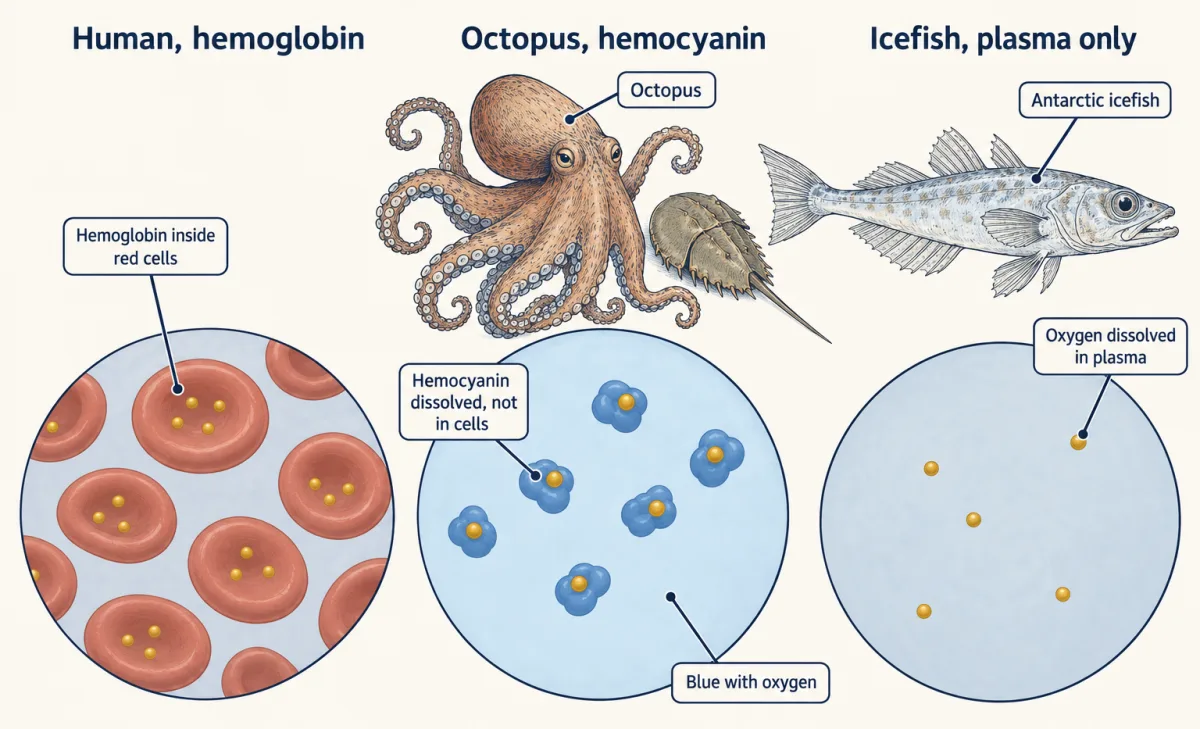
Other carriers, and none. Horseshoe crabs and octopuses carry oxygen on hemocyanin, a copper-containing protein dissolved in their blood rather than packed in cells; the fluid is called hemolymph in animals with an open circulation, such as horseshoe crabs, while octopuses have a closed circulation. It is colourless without oxygen and blue with it. Adult Antarctic icefish, family Channichthyidae, have no red cells and no working hemoglobin, as Johan Ruud reported in 1954. Their oxygen travels dissolved in plasma, in water near freezing that holds more dissolved gas than warm water.
Carrying carbon dioxide back
Carbon dioxide made in the tissues returns to the lungs in three forms. Textbooks give rough splits that differ between sources; one common one for an adult human puts about 5% dissolved, about 70% as bicarbonate and about 25% bound to hemoglobin. These fractions are approximations: they depend on conditions and differ along the path from tissue to lung.
Bicarbonate. In red cells, the enzyme carbonic anhydrase speeds the reaction of carbon dioxide with water (see enzyme action):
CO2 + H2O ⇌ H2CO3 ⇌ H+ + HCO3-
The bicarbonate leaves the red cell in exchange for a chloride ion through a membrane exchanger (see membrane transport), and it travels in plasma. The hydrogen ions are largely buffered by hemoglobin, and they are the source of part of the Bohr effect in tissue capillaries. In the lungs, where carbon dioxide is low, the reactions run backwards and carbon dioxide diffuses out to be exhaled.
Carbamino compounds. Some carbon dioxide binds directly to the end amino groups of hemoglobin’s chains, forming carbamino compounds. It does not bind the iron where oxygen sits. Experiments that blocked those amino groups in horse hemoglobin removed the oxygen-linked part of this binding.
The Haldane effect is the other side of Bohr’s linkage. At the same carbon dioxide pressure, deoxygenated blood carries more carbon dioxide than oxygenated blood; Christiansen, Douglas and Haldane described it in 1914. Deoxygenated hemoglobin buffers hydrogen ions better and forms more carbamino compounds. In the lungs, oxygenation releases hydrogen ions, which push bicarbonate back to carbon dioxide for exhalation. The Bohr effect is carbon dioxide and pH acting on oxygen binding; the Haldane effect is oxygen acting on carbon dioxide carriage. Bicarbonate also links to blood pH, which the kidney helps regulate.
Design problem
Human fetal blood binds oxygen more tightly than adult blood. Is that higher affinity built into fetal hemoglobin itself, or does it come from how fetal hemoglobin responds to BPG? Design an experiment to tell.
One way to do it
Separate the protein from its surroundings. Purify adult and fetal hemoglobin and strip both of BPG and other organic phosphates, as Bunn and Briehl did in 1970.
First, measure the P50 of each stripped hemoglobin. If fetal hemoglobin were much tighter-binding on its own, its P50 would already be lower here.
Second, add back the same BPG concentration to both. Bunn and Briehl used 0.2 mM BPG and found that adult P50 rose about twofold while fetal P50 rose less. A smaller rise for fetal hemoglobin points to a weaker BPG response as the explanation.
Hold everything else equal: pH, temperature, buffer, salt and hemoglobin concentration, since each changes P50. Measure several BPG concentrations to get a dose-response, not one point.
Then check the result in whole blood, comparing cord blood with adult blood, as Enoki and colleagues did in 1972. Finally, note the limit: test-tube conditions may be far from body temperature, so repeat the comparison at 37 degrees C before applying the numbers to a living fetus.
How we measure it
Gas equilibration (tonometry)
Expose a blood or hemoglobin sample to a gas mixture of known oxygen and carbon dioxide partial pressure until it comes to equilibrium, then measure the bound oxygen. Repeating it at many oxygen pressures traces the dissociation curve, and changing one gas at a time tests its effect.
Oxygen equilibrium spectrophotometry
Oxygenated and deoxygenated hemoglobin or myoglobin absorb light differently, so the spectrum of a sample gives its saturation. Fitting several wavelengths at once can also correct for oxidized pigment, as the 1997 horse myoglobin study did for metmyoglobin.
Phosphate stripping and add-back
Remove BPG and other organic phosphates from purified hemoglobin, then add back a known amount and measure the change in P50. Comparing two hemoglobins under identical conditions separates their built-in affinity from their response to the effector.
Chemical blocking of amino groups
React selected chain-end amino groups of hemoglobin with cyanate so they can no longer bind carbon dioxide, then compare carbon dioxide binding by the oxygenated and deoxygenated forms. If the difference vanishes, those groups carried it.
Finish line
Test yourself
8 questions
Practice and MCAT-style, with explained answers.
Next · Lesson 14
Digestive Systems and Nutrition
A dog eats a meal that falls out of its neck before it reaches the stomach, yet its stomach pours out acid. What told the stomach to start?
Continue →